01
Abbott · FreeStyle Libre

UX Audit & Lifecycle Experience Design

Reducing early adoption risk by identifying UX friction and redesigning the full patient lifecycle experience, from first touch through confident device use.

UX Audit Experience Design CRM Architecture Patient Lifecycle Medical Device
Abbott · Health Canada · CGM Onboarding
The content was right.
The timing was wrong.
↓ 20% drop-off · 12 friction points identified
Challenge
Right content, wrong timing — drop-off during the critical first-use period, with no lifecycle model to guide it.
Approach
Rebuilt the onboarding experience around behavioral readiness stages, not a content calendar.
Outcome
20% reduction in drop-off. 12 friction points identified and resolved, Health Canada MLR-compliant.
Problem & insight
Product & UX approach
Decision log
Deliverables
Hindsight
All case studies →
From brief to reframed problem

The brief came in as a content and communications problem. The diagnosis revealed something structurally different.

Client brief

"Improve the onboarding communications program — patients aren't engaging with the content we're sending them during device activation."

Reframed UX problem

This isn't a content engagement problem — it's a sequencing alignment failure. The communication architecture was built around a content calendar, not a patient readiness model. Patients were receiving advanced CGM management content before they'd established basic device confidence. The content was correct. The timing was wrong. The fix isn't better content — it's a lifecycle UX model built around behavioral readiness stages.

This reframe drove the entire service blueprint approach — moving from a calendar-driven CRM model to a readiness-staged behavioral sequencing system across 10 phases and 88 days.

Transferable to

Connected health device onboarding & wellness app retention. Identifying readiness-stage transition points and designing proactively around predicted drop-off moments applies to any connected health or wellness platform managing a critical first-use period — CGM, insulin pumps, remote monitoring, mental health apps, and fitness platforms all face the same lifecycle UX challenge.

Key insight

Drop-off clustered at two specific transitions, not randomly distributed. Drop-off spiked at week 1 post-activation (device confidence gap) and weeks 4–5 (lifestyle integration demand before habit was established). The calendar crossed both transitions without acknowledging them.

Product & UX approach

I treated this as a lifecycle alignment problem, not a content problem — mapping the behavioral and emotional arc across the first-use period and redesigning sequence, prioritization, and timing around it: device confidence first, lifestyle integration mid-arc, habit reinforcement late. Ten phases across 88 days, each with a defined behavioral objective.

Key design decisions
Decision point Alternatives considered What we chose & why
Program structure — calendar-based vs. behavior-triggered
Maintain the existing Day 1 / Day 3 / Day 7 calendar model with improved content.
Behavior-staged sequencing across 10 phases — the calendar model was the root cause of drop-off, since timing didn't match patient readiness.
Drop-off intervention — reactive vs. proactive
Reactive: detect inactivity, send re-engagement email after 7 days of non-use.
Proactive: Phases 4 and 7 targeted known drop-off risk points before inactivity occurred — prevention beat reactive re-engagement.
CRM as broadcast vs. two-way feedback instrument
Treat all emails as one-directional communications (simpler to build, easier through MLR).
Embedded in-email surveys at two transition points (E4 insurance status, E6 replacement readiness), turning the CRM into a listening channel, not just a delivery mechanism.
Email rendering — light-mode-only vs. dark-mode-aware
Maintain existing light-background templates; treat dark mode as an edge case handled by the mail client.
Rebuilt templates with dark-mode-aware tokens — inverted, low-contrast rendering in Apple Mail was hurting legibility for patients with low vision or light sensitivity, so accessibility was treated as a rendering requirement, not a polish pass.
Figure 01 · Audit DeliverablePatient readiness vs. content timing
Readiness stage Window Why it matters
Anxious Day 0–1 Device just received. Patient needs confidence, not feature education — highest-risk moment if activation stalls.
Uncertain Day 1–3 Building habits but not yet confident. Device errors or unresolved HCP connection can derail progress here.
Forming Day 3–40 The behavioral loop forms or fails here. Average churn point falls within this window — intervention timing is critical.
Building Day 40–60 Consistent scan frequency by this point predicts retention. Community and social proof become relevant for the first time.
Confident Day 60–88 Patient is self-managing. Focus shifts to insurance, community, and programme graduation.
Reframe
Assumed: the content wasn't engaging enough. Found: the content was clinically accurate — the sequencing was wrong. Patients received the right information at the wrong point in their adoption stage.
↓20%
Patient drop-off reduction
12
Friction points identified
5
Readiness stages mapped
3
CRM streams resequenced

This patient readiness vs. content timing analysis was the foundational audit deliverable — it identified the sequential gap that produced the 20% drop-off. Five patient readiness stages mapped against actual CRM content delivery timing, with a 12-point friction inventory across sequencing, content architecture, CTA logic, and support visibility.

This deliverable reframed the project scope — moving the client from 'improve content' to 'rebuild the sequence,' unlocking a full service blueprint engagement rather than a copy refresh.
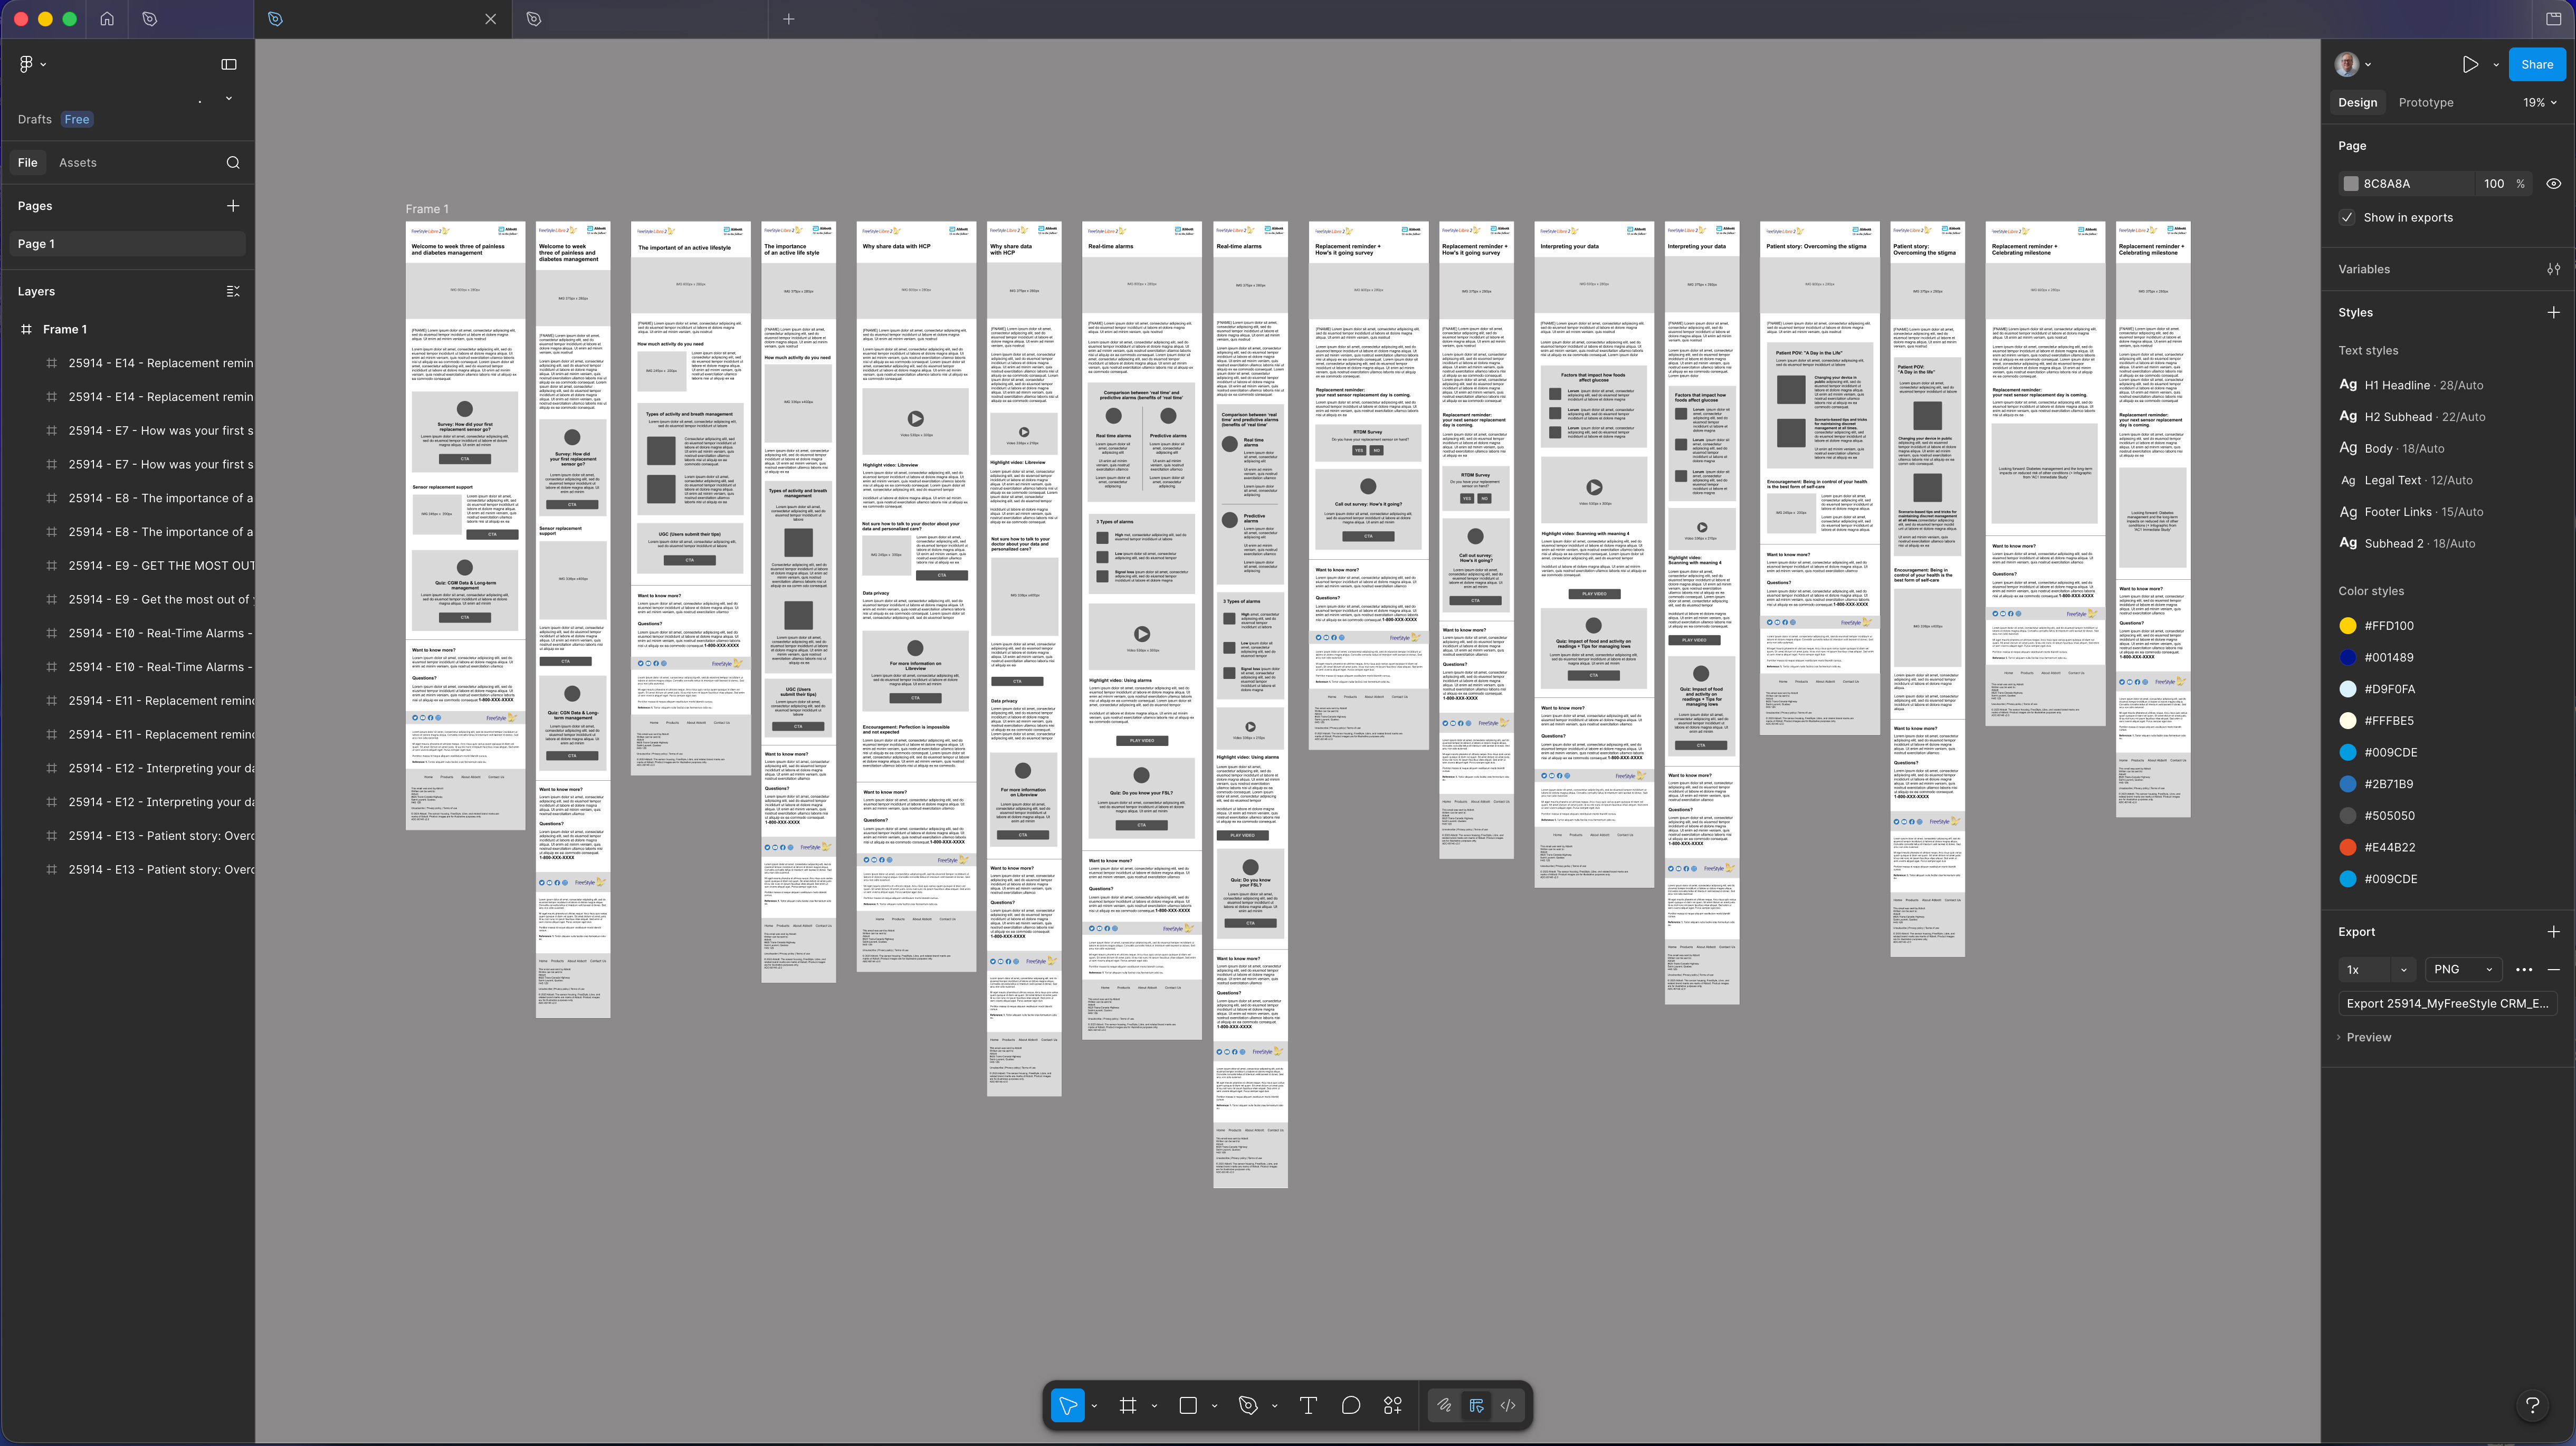
Figure 02 · Deliverable
Full CRM Wireframe Suite

Fourteen email frames spanning the 88-day lifecycle arc, including A/B subject line variants and paired desktop/mobile layouts. Mid-fidelity delivery designed for MLR review alignment and development handoff, covering the complete programme sequence from device activation through graduation with consistent type styles, color tokens, and component states.

Delivered directly into MLR submission, eliminating a second design pass and compressing the Health Canada review timeline.

Figure 03 · DeliverableService blueprint — 10-phase lifecycle arc
# Phase Window Risk
Batch 1 — Early activation & first-use confidence
01ActivationDay 0–1
02First ScanDay 1–3
03Habit BuildingDay 3–8
04Sensor ExpiryDay 11–13Critical
Batch 2 — Habit formation, retention & long-term engagement
05Getting StartedDay 15–25
06Churn DecisionDay 25–40Critical
07Habit Lock-InDay 40–60High
08Social & ProofDay 45–60
09ContinuityDay 60–86
10GraduationDay 80–88High
10
Phases
88
Days
6
Risk moments
2
Batches
↓20%
Patient drop-off — audit-driven intervention

Service blueprint — UX lifecycle architecture. The FreeStyle Libre CRM onboarding service blueprint defined the full patient lifecycle UX arc — establishing the phase structure, behavioral sequencing, and experience design logic across an 88-day engagement program.

Became the exec-ready brief that held the room without a UX translator — clinical, regulatory, and brand stakeholders could read and act from it directly.

Figure 04 · DeliverableThree-stream CRM architecture audit
Root cause
The experience gap was sequential, not informational. Across all three streams, patients received clinically accurate content at the wrong point in the adoption arc. Resequencing to patient readiness — not new content — directly addressed the Week 1–2 drop-off.
Stream Scope Key finding
Onboarding Day 1–88 · 23 emails · 3 batches Primary audit focus — activation through programme graduation. See Figures 01–03.
Getting Started Pre-activation No readiness-staged sequencing and no HCP-led content before activation — reduces confidence and clinical credibility at first use.
Prospect Pre-subscription CGM category awareness thin and FSL2 differentiation underdeveloped — no introduction layer for BGC-only patients.
↓20%
Retention target
3
CRM streams audited
23
Onboarding emails
88
Day programme arc

Lifecycle communication experience design — translated the service blueprint into a complete experience design architecture spanning the full onboarding arc. Early communications established device confidence; mid-arc introduced lifestyle integration; later-stage shifted toward habit reinforcement and long-term self-management behaviors.

Translated the service blueprint into an actionable delivery sequence the CRM team could execute without UX present in every sprint.

Role
UX strategy & experience design lead — lifecycle framework, CRM architecture, behavioral sequencing, service blueprint
Collaboration
Led agency-side across UX, strategy, and account before engaging Abbott's clinical, regulatory, and digital teams — every deliverable arrived as a stress-tested recommendation, not an open question.
Deliverables
UX audit, wireframe suite, service blueprint, CRM architecture, MLR-approved assets
Regulatory context
Health Canada
Industry
Medical devices · Continuous glucose monitoring
What I'd sharpen

The 10-phase behavioral model held up as the right architecture. The gap was downstream: no feedback loop let the phase sequence branch on actual engagement signals — patients showing device confidence early should have advanced faster, patients showing inactivity should have hit a different intervention path before Phase 4. The data existed. The CRM wasn't built to act on it. I'd also bring HCP-side journey design in earlier — the intersection between patient onboarding and prescriber communication is where the sharpest alignment gains are.